Category: Cleveland

  • Dark Spots on Skin After Summer: 5 Essential Facts About Hyperpigmentation

    Dark Spots on Skin After Summer: 5 Essential Facts About Hyperpigmentation

    Dark spots on skin are one of the most common concerns patients bring to a dermatologist at the end of summer. A patch on the cheek that was not there in May. A cluster of brown marks across the back of the hands. A streak of discoloration on the forehead that appeared gradually and has no intention of fading on its own. These marks go by different names depending on the cause, including sun spots, age spots, melasma, and post-inflammatory hyperpigmentation, but they all share one thing in common: they change the way your skin looks, and that change can be concerning.

    The question most patients ask is straightforward: is this something I should worry about? The answer depends entirely on what is causing the discoloration. Some dark spots on skin are purely cosmetic. Others are warning signs of sun damage that could progress. A board-certified dermatologist can tell the difference in a single visit, and that distinction matters more than any over-the-counter product ever will.

    What Causes Dark Spots on Skin?

    Dark spots form when the skin produces excess melanin, the pigment that gives skin its color. This overproduction can be triggered by several different factors, and understanding the cause is the first step toward effective treatment.

    Sun exposure is the most common trigger. Ultraviolet radiation stimulates melanocytes, the cells that produce melanin, to ramp up production as a defense mechanism against UV damage. Over time, this leads to concentrated deposits of pigment in areas that get the most sun: the face, hands, forearms, chest, and shoulders. These marks are often called solar lentigines, or more commonly, sun spots or age spots. They tend to appear after age 40 but can show up earlier in people with significant cumulative sun exposure. After a full summer of outdoor activity, whether on the lake, at the golf course, or just spending time in the yard, these spots become noticeably darker and more visible.

    Melasma is a different type of hyperpigmentation that produces larger, blotchy patches of brown or grayish-brown discoloration, usually on the cheeks, forehead, bridge of the nose, and upper lip. It is driven primarily by hormonal changes and is significantly worsened by sun exposure. Women are affected far more often than men, and pregnancy, oral contraceptives, and hormone replacement therapy are common triggers. Melasma is sometimes called the mask of pregnancy because of how frequently it develops during that time. The summer months make melasma visibly worse because UV exposure intensifies the pigmentation, even with sunscreen use.

    Post-inflammatory hyperpigmentation, or PIH, occurs when the skin darkens in an area where there was a previous injury or inflammation. Acne lesions, bug bites, cuts, burns, eczema flares, and even aggressive skin treatments can leave behind dark marks as the skin heals. PIH is more common and more noticeable in patients with darker skin tones. It is not a scar in the structural sense, but it can take months to fade without treatment.

    When Dark Spots on Skin Could Be Something More Serious

    Most dark spots on skin are benign, but not all of them. This is the part that makes a professional evaluation worth the visit. A spot that looks like a harmless sun spot to an untrained eye can sometimes be an actinic keratosis, a precancerous lesion caused by cumulative UV damage. In rarer cases, a dark spot could be lentigo maligna, a type of melanoma that appears on chronically sun-damaged skin and can closely mimic a benign sun spot in its early stages.

    The signs that should prompt a visit to a dermatologist include any dark spot that is new and growing, a spot with irregular borders or multiple colors within it, a mark that bleeds, itches, or crusts, or a patch that looks different from the other spots on your skin. The ABCDE criteria used for evaluating moles also apply here: asymmetry, border irregularity, color variation, diameter greater than six millimeters, and evolution over time. If any of these features are present, a dermatologist should evaluate the spot promptly.

    Dermatologists use dermatoscopy, a magnified examination with polarized light, to evaluate suspicious spots with a level of detail that is not possible with the naked eye. If a biopsy is warranted, it can be performed the same day, and results are typically available within one to two weeks.

    How a Dermatologist Treats Dark Spots on Skin
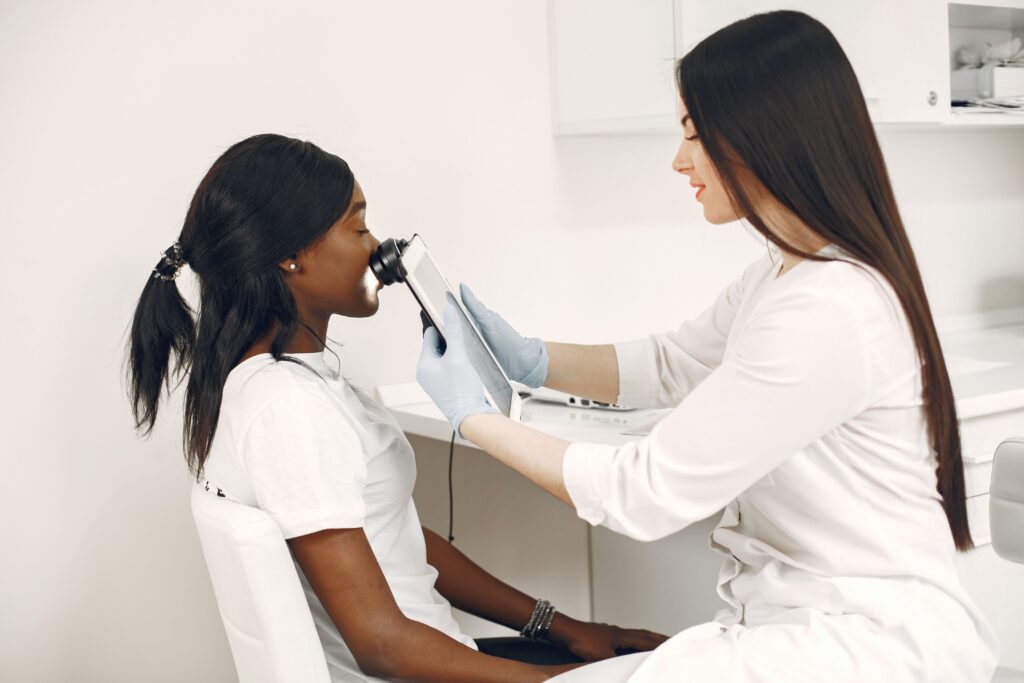
    Dermatology provider examining a patient’s facial dark spots with a digital dermatoscope
    A professional skin examination can distinguish cosmetic hyperpigmentation from spots that may require medical attention.

    Treatment depends on the type, depth, and cause of the pigmentation. There is no single product or procedure that works for every kind of dark spot, which is why a professional diagnosis is the necessary first step.

    For sun spots and solar lentigines, cryotherapy with liquid nitrogen is a common and effective office-based treatment. The liquid nitrogen freezes the excess pigment, and the treated spot darkens, crusts, and peels away over one to two weeks, revealing more evenly toned skin underneath. For patients with widespread sun damage across a larger area, prescription topical treatments such as hydroquinone, tretinoin, or a combination formulation can be applied at home over several weeks to gradually lighten the discolored skin.

    Melasma requires a different and more careful approach because it is driven by internal factors like hormones as well as external triggers like UV exposure. First-line treatment typically involves a combination of topical agents: hydroquinone to suppress melanin production, a retinoid to increase cell turnover, and a mild corticosteroid to reduce inflammation. This triple combination therapy has strong clinical evidence behind it. Strict and consistent sun protection is essential for melasma patients because even brief unprotected sun exposure can undo weeks of treatment progress.

    Post-inflammatory hyperpigmentation often improves on its own over time, but that timeline can stretch to six months or longer without intervention. Topical treatments containing ingredients like hydroquinone, azelaic acid, vitamin C, or niacinamide can accelerate fading. Addressing the underlying cause of the inflammation, whether that is acne, eczema, or another condition, is equally important to prevent new marks from forming as old ones fade.

    What Over-the-Counter Products Can and Cannot Do

    Drugstore brightening products work for some patients with mild, superficial discoloration. Products containing vitamin C, niacinamide, alpha hydroxy acids, or licorice root extract can produce gradual improvement when used consistently over several weeks. These are reasonable options for patients with minor unevenness who want to try something before seeing a dermatologist.

    What over-the-counter products cannot do is diagnose what is causing the dark spots on skin. A spot that is actually an actinic keratosis will not respond to a brightening serum and needs medical treatment. A patch of melasma requires a targeted prescription approach that addresses the hormonal component. Using the wrong product on the wrong type of discoloration can sometimes make things worse, particularly products that irritate the skin and trigger more inflammation, which leads to more post-inflammatory hyperpigmentation in a frustrating cycle.

    If you have tried over-the-counter products for six to eight weeks without noticeable improvement, or if you are not sure what kind of dark spots you have, a dermatologist can clarify the diagnosis and recommend a treatment that actually matches the problem.

    The Role of Sun Protection in Preventing Dark Spots on Skin

    Man applying sunscreen to his face while looking in a car window at the beach
    Daily broad-spectrum sunscreen helps prevent sun spots and keeps existing hyperpigmentation from becoming darker.

    Every type of hyperpigmentation is made worse by UV exposure, which means sun protection is both prevention and treatment. Broad-spectrum sunscreen with SPF 30 or higher, applied daily to all exposed skin and reapplied every two hours when outdoors, is the single most important thing a patient with dark spots on skin can do. This applies year-round, not just during the summer months.

    For patients actively treating hyperpigmentation, sun protection is non-negotiable. Prescription lightening agents will not produce lasting results if the skin continues to be exposed to UV radiation without adequate protection. Dermatologists recommend mineral sunscreens containing zinc oxide or titanium dioxide for patients with melasma because these physical blockers provide immediate, broad-spectrum coverage without the irritation that some chemical filters can cause.

    Woman wearing a wide-brimmed straw hat to protect her face from the sun
    Wide-brimmed hats provide an additional layer of protection against the UV exposure that can worsen hyperpigmentation.

    Wide-brimmed hats, UV-protective sunglasses, and seeking shade during peak UV hours between 10 a.m. and 4 p.m. add meaningful layers of defense. In Southeast Tennessee, where outdoor activity runs well into October, maintaining sun protection habits through the fall is just as important as the summer routine.

    Schedule an Appointment

    If you have dark spots that appeared or worsened this summer, a professional evaluation takes the guesswork out of what you are dealing with and what will actually work to treat it. The board-certified dermatologists at Chattanooga Skin and Cancer Clinic have been serving patients across the Tennessee Valley since 1973. Our Cleveland office is located at 3891 Adkisson Drive, Cleveland, TN 37312, and is open Monday through Friday, 7:30 a.m. to 4:30 p.m. EST. Visit our contact page to request an appointment or call 423-479-8648 to schedule.

    Follow us! @chattskinandcancer
  • Back-to-School Skin Check: 7 Issues Your Dermatologist Can Catch Before the First Bell

    Back-to-School Skin Check: 7 Issues Your Dermatologist Can Catch Before the First Bell

    A back-to-school skin check is one of the smartest things you can add to your child’s August to-do list, and it takes less time than most school supply runs. Between sports physicals, new shoes, and fresh notebooks, skin health tends to fall to the bottom of the priority list. But when a child walks into the classroom with an itchy rash, a wart on their hand, or acne that has been building all summer, it can affect their confidence, their comfort, and in some cases their ability to participate in sports and activities.

    At Chattanooga Skin and Cancer Clinic’s Cleveland, TN office on Adkisson Drive, our board-certified dermatologists see a wave of pediatric and adolescent skin concerns every August. Many of them could have been resolved quickly if caught a few weeks earlier. Here are seven common issues a back-to-school skin check can identify and treat before the first day of class.

    1. Acne That Got Worse Over the Summer

    Teen applying acne treatment to face before back-to-School skin check dermatologist visit in Cleveland TN
    Summer breakouts can escalate quickly. A dermatologist can evaluate whether over-the-counter products are enough or if a prescription-strength treatment is needed before school starts.

    Summer in Bradley County means heat, humidity, sweat, and sunscreen, all of which can push acne from mild to moderate in a matter of weeks. Teens who spent the summer at sports camps, working outdoor jobs, or swimming in chlorinated pools often come back with breakouts in new places: the jawline, chest, back, and hairline.

    A dermatologist can evaluate whether over-the-counter products are enough or whether a prescription-strength treatment, like a topical retinoid or an oral antibiotic, is needed to get things under control before school pictures and social pressures kick in. Starting treatment in August gives the skin several weeks to respond before fall activities are in full swing.

    2. Eczema Flares That Need an Updated Plan

    Children with eczema often experience a shift in triggers between summer and the school year. Summer flares tend to come from sweat, chlorine, and sun exposure. Once school starts, indoor heating, dry air, scratchy uniforms, and stress become the drivers. A back-to-school skin check gives your dermatologist the chance to adjust your child’s treatment plan before the seasonal shift happens.

    This might mean switching from a lighter summer moisturizer to a heavier barrier cream, updating a prescription, or creating a simplified routine your child can manage independently during the school day.

    3. Warts on Hands and Feet

    Warts are caused by the human papillomavirus (HPV) and spread easily in warm, moist environments like pools, locker rooms, and shared gym equipment. Children who spent the summer barefoot at the pool or walking around camp are especially prone to picking up plantar warts on the soles of their feet or common warts on their fingers.

    The problem with waiting is that warts multiply. A single wart in July can become a cluster by September. A dermatologist can treat warts quickly with cryotherapy or other in-office methods, and the earlier they are addressed the easier they are to resolve.

    4. Fungal Infections from Summer Activities

    Ringworm, athlete’s foot, and jock itch are all fungal infections that thrive in the heat and humidity of a Tennessee summer. Kids who play contact sports, share towels, or wear damp athletic gear for extended periods are at higher risk. These infections are contagious and can spread quickly in a school environment through shared mats, equipment, and locker rooms.

    During a back-to-school skin check, a dermatologist can diagnose fungal infections that might look like a simple rash to an untrained eye and prescribe antifungal treatment that clears the issue before your child is back in close contact with classmates.

    5. Suspicious Moles or New Growths

    Close-up of moles on skin checked during back to school skin check in Cleveland TN
    Mole Check Back to School Skin Exam Cleveland TN

    Children and teens develop new moles as they grow, and most of them are completely harmless. But after a summer of increased sun exposure, it is worth having a dermatologist look at anything new or changed. Pediatric melanoma is rare, but atypical moles identified early can be monitored or removed before they become a concern.

    A back-to-school skin check is an easy opportunity to get a baseline evaluation of your child’s moles, especially if there is a family history of skin cancer or if your child has fair skin and a history of sunburns.

    6. Contact Dermatitis from New Products or Gear

    New school supplies, new laundry detergent for uniforms, new hair products for the first day, new shin guards or cleats for fall sports. August is full of “new,” and any of these can trigger contact dermatitis in children with sensitive skin. The reaction might show up as a red, itchy patch on the wrist from a new watchband, or as irritation on the legs from new fabric softener.

    If your child has a history of skin sensitivity or allergic reactions, a quick dermatology visit can help identify the trigger and recommend alternatives so the reaction does not carry over into the school year.

    7. Molluscum Contagiosum

    Molluscum contagiosum is a viral skin infection that causes small, flesh-colored or pink bumps, often in clusters. It is extremely common in children under ten and spreads through direct skin-to-skin contact or shared items like towels and clothing. Pools and water parks are common sources of transmission during the summer months.

    While molluscum sometimes resolves on its own, it can take months or even a year to clear completely. A dermatologist can treat the bumps in the office and help prevent the spread to siblings, classmates, and teammates.

    Why a Back-to-School Skin Check Matters More Than You Think

    Skin issues in children are easy to underestimate. A rash seems minor until it does not go away. A few pimples feel manageable until they become painful cysts. A wart seems harmless until it spreads to three more fingers. The common thread is that early intervention is almost always faster, simpler, and less disruptive than waiting.

    A back-to-school skin check also gives parents a chance to ask questions they have been putting off. Is that dry patch on my child’s elbow just dry skin, or is it psoriasis? Should we be worried about the mole behind their ear? Is their acne routine actually working? These are the kinds of questions a board-certified dermatologist can answer in a single visit.

    Schedule a Back-to-School Skin Check in Cleveland, TN

    Chattanooga Skin and Cancer Clinic’s Cleveland office is located at 3891 Adkisson Drive, Cleveland, TN 37312, and serves families across Bradley County and the surrounding region. Our board-certified dermatologists provide pediatric and adolescent dermatology services Monday through Friday, 7:30 AM to 4:30 PM EST.

    Call 423-479-8648 to schedule your child’s back-to-school skin check today. August appointments fill quickly, so we recommend booking early to get your preferred time before the school year begins.

    FOLLOW US! @chattskinandcancer

  • Teen Sports Acne in Summer: 6 Ways to Stop Breakouts Before They Start

    Teen Sports Acne in Summer: 6 Ways to Stop Breakouts Before They Start

    Teen sports acne in summer is one of the most common skin complaints dermatologists treat between June and August. Double practices, sports camps, and hours under a helmet or pads in the heat create breakouts that seem to multiply no matter what a teenager does to fight them. This is not a hygiene problem and it is not something kids grow out of on their own schedule. It is a predictable skin response to heat, sweat, friction, and the hormonal changes already happening during adolescence. The combination creates a perfect storm for clogged pores and inflamed skin.

    If your teen is dealing with acne that gets worse during their sport season, understanding the specific causes helps target the right solutions. Generic face wash advice only goes so far when the real triggers include chin straps, shoulder pads, and two-a-day practices in 90-degree heat. At Chattanooga Skin and Cancer Clinic’s Cleveland office, our dermatologists treat teens across the age spectrum for sports-related skin conditions, and summer is our busiest season for these visits.

    What Causes Teen Sports Acne in Summer?

    Acne develops when pores become clogged with a mix of dead skin cells, oil, and bacteria. Hormones during puberty increase oil production in the skin, which is why teenagers are more prone to breakouts than adults. Add the summer sports environment, and every factor that contributes to acne intensifies.

    Teen athletes playing soccer in summer heat where sweat and friction can cause sports acne
    Summer sports like soccer combine heat, sweat, and skin-to-skin contact, all of which contribute to breakouts in teen athletes.

    Heat increases oil production. When body temperature rises, sebaceous glands ramp up output to help cool the skin. That extra oil mixes with sweat and dead skin cells on the surface, filling pores faster than they can clear themselves. Humidity slows the evaporation of sweat, keeping that oil-and-sweat mixture sitting on the skin longer.

    Sweat itself does not directly cause acne, but it creates the conditions for it. Salt and minerals in sweat irritate pore linings when left on the skin, promoting inflammation. Bacteria that contribute to acne, particularly Cutibacterium acnes, thrive in warm, moist environments. A sweaty jersey pressed against the chest and back for hours gives those bacteria exactly what they need. This is why teen sports acne in summer tends to concentrate on the chest, back, and shoulders rather than just the face.

    What Is Acne Mechanica and Why Does It Affect Athletes?

    Acne mechanica is a specific form of acne caused by friction, pressure, and heat against the skin. It is the type of breakout most closely associated with sports. Helmets cause it along the forehead and jawline. Chin straps produce a ring of pimples along the chin and cheeks. Shoulder pads trigger it across the upper back and shoulders. Even headbands, sports bras, and tight compression shorts can cause acne mechanica in the areas they press against.

    The friction disrupts the skin’s surface and pushes dead cells and oil into pores, while the pressure prevents those pores from clearing naturally. When you add heat and sweat underneath the equipment, the trapped moisture softens the skin and makes it more susceptible to bacterial invasion. According to dermatology research published in the Cutis journal, acne mechanica is one of the most underrecognized forms of acne in the athletic population, because patients and parents assume it is ordinary teenage acne and do not mention the sports connection to their doctor. Recognizing acne mechanica as a distinct condition is one of the first steps to managing teen sports acne in summer effectively.

    The location of the breakout is the giveaway. If acne clusters specifically where equipment contacts the skin and worsens during the sport season, acne mechanica is the likely diagnosis.

    How Can Teen Athletes Reduce Breakouts During the Season?

    Timing is the most effective tool for controlling teen sports acne in summer. Showering within 20 minutes of finishing practice or a game makes a measurable difference. The longer sweat, oil, and bacteria sit on the skin after exercise, the more damage they do. A full shower is ideal, but at minimum, using a gentle cleanser on the face, chest, and back immediately after activity removes the worst of the buildup.

    The cleanser matters. A body wash or facial cleanser with two percent salicylic acid helps dissolve the oil and dead skin cells that clog pores. Benzoyl peroxide in a wash formula, at a concentration of five percent or lower, kills acne-causing bacteria on contact. These are available over the counter and are safe for daily use in teenagers. Avoid harsh scrubs or rough washcloths, which irritate the skin and make acne mechanica worse by adding more friction.

    Teen washing face with gentle cleanser to manage sports acne after summer practice
    A gentle cleanser with salicylic acid or benzoyl peroxide after practice helps clear the sweat, oil, and bacteria that cause summer sports breakouts.

    Clothing and equipment management plays a bigger role than most families realize. Wear moisture-wicking base layers under pads and helmets. Wash sports bras, compression shirts, and any fabric that contacts the skin after every use, not after every few uses. Wipe down the inside of helmets and pads with antibacterial wipes between practices. Letting equipment air out completely between sessions reduces bacterial buildup. Parents who stay on top of laundry and gear maintenance give their teen a real advantage against teen sports acne in summer.

    Keep hands off the face during practice and games. Athletes constantly wipe sweat from their foreheads and touch their faces with dirty gloves or hands, transferring bacteria directly into pores. A clean towel draped around the neck gives them something to reach for instead.

    What Role Does Diet Play in Teen Sports Acne?

    Diet’s connection to acne has been studied extensively, and the evidence points to two main factors. High-glycemic foods, those that spike blood sugar quickly like white bread, sugary sports drinks, candy, and processed snacks, appear to increase oil production and inflammation in the skin. A study published in the Journal of the Academy of Nutrition and Dietetics found a positive association between high-glycemic diets and acne severity in young adults.

    Dairy, particularly skim milk, has also been linked to increased acne in some studies, though the mechanism is not fully understood. Hormones naturally present in milk may interact with the hormones driving oil production during puberty. This does not mean every teenager needs to eliminate dairy, but if breakouts are persistent and not responding to topical treatments, dietary patterns are worth discussing with a dermatologist. For many teens, cleaning up their nutrition alongside a proper skin care routine is what finally gets teen sports acne in summer under control.

    Hydration with water instead of sugary or caffeinated beverages supports skin health during intense physical activity. Proper hydration keeps the body’s cooling system working efficiently and reduces the concentration of irritants in sweat.

    When Should Parents Bring Their Teen to a Dermatologist?

    Over-the-counter products handle mild acne well, but there are clear signs it is time for professional help. If breakouts are leaving dark marks or scars, that damage is worth preventing with stronger treatment. If acne covers the back, chest, and face and is not improving after six to eight weeks of consistent home care, a dermatologist can prescribe targeted therapies that work faster and more effectively. Teen sports acne in summer that does not respond to drugstore products within that window needs a clinical evaluation.

    Cystic acne, the deep, painful nodules that sit under the skin, rarely responds to drugstore products. These lesions carry a higher risk of permanent scarring and need prescription-level intervention. Teenagers sometimes minimize their acne or resist bringing it up, so parents should pay attention to changes in behavior, avoidance of activities, and visible scarring that suggest the condition is affecting quality of life.

    At the Cleveland office, we see patients from age 12 through adulthood for acne management. Treatment plans account for the specific demands of the patient’s sport, their schedule, and what they are realistically going to follow through on. A complicated ten-step routine does not help a 14-year-old who rushes through everything.

    What Prescription Treatments Work for Sports-Related Acne?

    Topical retinoids are a cornerstone treatment. They increase skin cell turnover, preventing dead cells from accumulating in the pore. Adapalene, available both over the counter and in prescription strengths, is a common starting point. It pairs well with benzoyl peroxide for a combination approach that targets both clogged pores and bacteria.

    Topical or oral antibiotics may be prescribed for moderate inflammatory acne. These are used for defined periods to reduce bacterial load and inflammation, not as permanent solutions. For female athletes dealing with hormonal acne patterns, oral contraceptives or spironolactone are sometimes appropriate, depending on age and overall health. Your dermatologist will match the prescription to the severity and type of teen sports acne your child is experiencing in summer.

    In severe cases, isotretinoin, commonly known by its former brand name Accutane, is the most effective treatment available. It reduces oil production dramatically and can produce long-lasting clearance. It requires close monitoring with monthly blood tests and, for female patients, pregnancy prevention measures. It is reserved for cases where other treatments have not succeeded, but for the right patient, it can be life-changing.

    Frequently Asked Questions About Teen Sports Acne in Summer

    Does Sunscreen Make Sports Acne Worse?

    It can if you use the wrong product. Heavy, oil-based sunscreens clog pores, especially under equipment. Choose a lightweight, non-comedogenic, oil-free mineral sunscreen. Apply it 15 minutes before practice and reapply as needed.

    Can Swimming Help Clear Up Acne?

    Chlorine has mild antibacterial properties, but it also dries and irritates the skin, which can worsen acne over time. Rinse off immediately after swimming and apply a gentle moisturizer. Do not rely on pool water as a treatment.

    Should Teen Athletes Use Acne Products Before Practice?

    Active treatments like benzoyl peroxide and retinoids are best applied at night after the skin is clean. Using them before practice can cause irritation when combined with sweat and friction. A gentle cleanser and lightweight moisturizer or sunscreen are all that is needed before activity.

    How Long Does It Take for Sports Acne to Improve with Treatment?

    Most acne treatments take six to eight weeks to show visible improvement. Starting a treatment plan before the sport season begins gives it time to take effect. If your teen has a camp or season starting in July, scheduling a dermatology appointment in May or early June puts you ahead of the problem.

    Is Sports-Related Acne Different from Regular Teenage Acne?

    The underlying causes overlap, but acne mechanica has distinct triggers related to equipment friction and heat trapping. A dermatologist who understands the sports connection can tailor the treatment plan accordingly, which leads to faster improvement than a generic acne approach.

    Teen sports acne in summer does not have to be an accepted part of being a young athlete. The right combination of hygiene habits, equipment care, and, when needed, professional treatment keeps skin manageable even during the most intense stretches of the season. Chattanooga Skin and Cancer Clinic’s Cleveland office at 3891 Adkisson Drive, Cleveland provides dermatology care for teens and young athletes across the Cleveland, Jasper, and surrounding communities. Call 423.479.8648 to schedule a visit.

  • Chlorine Skin Irritation in Kids: Is Pool Water Bad for Your Child’s Skin?

    Chlorine Skin Irritation in Kids: Is Pool Water Bad for Your Child’s Skin?

    Chlorine keeps pool water safe by killing harmful bacteria and preventing waterborne illness. It does its job well. But the same chemical properties that make chlorine effective as a disinfectant also make it harsh on skin, and children’s skin is more vulnerable to that harshness than an adult’s. If your child has been coming home from the pool with dry, itchy, red, or flaking skin, the chlorine is the most likely cause. Chlorine skin irritation in kids is one of the most common summer complaints pediatric dermatologists hear.

    Pool season in Southeast Tennessee runs hot and long. Kids may be in the water four or five days a week between swim team, summer camp, and family trips to the neighborhood pool. That level of exposure adds up. Understanding how chlorine affects your child’s skin and what you can do about it lets your family enjoy the water without paying for it later in rashes, dryness, and discomfort. At Chattanooga Skin and Cancer Clinic’s Cleveland office, we treat children of all ages for summer skin issues, and pool-related irritation is at the top of the list from June through August.

    What Causes Chlorine Skin Irritation in Kids?

    Chlorine is an oxidizer. It works by breaking down organic matter on contact, which is how it neutralizes bacteria in pool water. But it does not distinguish between harmful microbes and the natural oils and proteins that protect your child’s skin. When a child sits in chlorinated water, the chemical strips away the skin’s lipid layer, the thin film of natural oils that keeps moisture locked in and irritants locked out.

    Children’s skin is thinner than adult skin and produces less natural oil. That makes the lipid barrier easier to disrupt and slower to recover. After even a single pool session, a child’s skin can lose enough of its protective layer to feel tight, dry, and rough. Repeated exposure without proper aftercare compounds the damage, resulting in cracking, flaking, and persistent itchiness that can last for days between swim sessions.

    The pH of pool water also plays a role. Well-maintained pools keep their pH between 7.2 and 7.8, which is close to neutral and relatively gentle. But many public and neighborhood pools fluctuate outside that range, especially during heavy-use periods. Water that is too acidic or too alkaline intensifies irritation and speeds up the breakdown of the skin barrier.

    Child swimming in chlorinated pool water during summer with sun hat and float
    Frequent pool visits during summer can strip natural oils from children’s skin, making post-swim rinsing and moisturizing a must.

    What Does Chlorine Irritation Look Like on a Child?

    The most common presentation is dry, rough patches of skin that appear after swimming and worsen with repeated exposure. The skin may look slightly red or feel bumpy, similar to mild sandpaper. Itching is the hallmark symptom, and children who scratch at irritated skin risk breaking it open, which creates an entry point for infection.

    Chlorine rash, sometimes called “swimming pool rash” by parents, presents as red, itchy patches or small bumps concentrated on areas the swimsuit did not cover. It differs from a bacterial rash called hot tub folliculitis, which produces pus-filled bumps caused by the Pseudomonas aeruginosa bacterium and is most often associated with inadequately chlorinated hot tubs and spas rather than properly maintained pools.

    In children with pre-existing eczema, chlorine exposure can trigger a full flare. The skin becomes inflamed, weepy, or cracked in areas that were previously stable. A study published in the British Journal of Dermatology found that children with atopic dermatitis experienced worsened skin barrier function after swimming in chlorinated pools compared to non-chlorinated water. For these kids, prevention strategies need to be more aggressive.

    Does Chlorine Cause Long-Term Damage to Skin?

    Occasional pool use does not cause lasting skin damage in healthy children. The skin’s lipid barrier regenerates, and short-term dryness resolves with basic moisturizing care. The concern arises with frequent, prolonged exposure without protective measures. Children on competitive swim teams who train daily may experience chronic dryness, contact dermatitis, and worsening of underlying conditions like eczema over the course of a full season.

    Chlorine can also affect hair and nails. Hair becomes brittle, dry, and may take on a greenish tint from copper compounds in pool water reacting with chlorine. Nails can become discolored or brittle with prolonged exposure. These effects reverse once the exposure stops, but they are a visible indicator that the chemical is making contact with the body’s keratin structures.

    What Steps Protect Your Child’s Skin Before and After Swimming?

    Pre-swim preparation makes a bigger difference than most parents expect. Have your child shower with fresh water immediately before getting into the pool. Wet skin absorbs less chlorinated water than dry skin. Think of it like a sponge: a dry sponge soaks up everything it contacts, while a damp sponge resists new liquid. Rinsing first reduces the amount of chlorine the skin takes in during the swim.

    Applying a thin layer of petroleum jelly or a barrier cream to areas prone to irritation, like the face, underarms, and inner thighs, creates a physical shield between the skin and the water. This works particularly well for children with eczema who need extra protection. Some parents apply a fragrance-free body oil before swimming to add a layer of protection; coconut oil and sunflower seed oil are popular options, though individual tolerance varies.

    Parent applying skin protection to child before swimming to prevent chlorine skin irritation
    Applying a barrier cream or moisturizer before swimming helps reduce chlorine contact with your child’s skin.

    Immediately after swimming, rinse your child off with fresh water. Do not wait until you get home. The sooner the chlorine comes off, the less time it has to continue stripping the skin. Use a gentle, fragrance-free soap or body wash to remove the chemical residue. Avoid hot water, which dries the skin further. Lukewarm is best.

    Within three minutes of getting out of the rinse, apply a thick, fragrance-free moisturizer to the entire body. Creams and ointments outperform lotions for post-swim recovery because they contain a higher ratio of oil to water, which seals moisture into the skin more effectively. Apply it to damp skin, which traps water against the surface and gives the moisturizer a base to lock in.

    What About Saltwater Pools and Alternatives?

    Saltwater pools are marketed as gentler alternatives, and there is some truth to that. These pools still use chlorine, generated by a salt-chlorine generator rather than added manually, but the concentration is lower than in traditional pools. The salt content also makes the water feel softer on the skin. Many children with chlorine sensitivity tolerate saltwater pools better, though they are not chlorine-free and can still cause irritation with extended use.

    UV and ozone pool sanitation systems reduce the amount of chlorine needed, which may benefit sensitive-skinned children. However, these systems are not yet common in public pools and community facilities. If your child has significant chlorine sensitivity, asking about the pool’s sanitation method before committing to a full summer of swim lessons can help you make an informed choice and prevent chlorine skin irritation.

    When Should You Take Your Child to a Dermatologist for Pool-Related Skin Issues?

    If your child’s post-swim skin irritation does not improve with consistent rinsing and moisturizing, it is time for a professional evaluation. Persistent redness, cracking, bleeding, or signs of infection like warmth, swelling, or pus indicate that the skin barrier has been compromised in a way that home care alone cannot fix. A dermatologist can prescribe targeted treatments to repair the barrier and reduce inflammation.

    Children with eczema who want to swim competitively need a management plan built around their swim schedule. This may include prescription barrier repair creams, modified moisturizing routines, and occasional use of topical anti-inflammatory medications after high-exposure days. Building that plan before the season starts prevents chlorine skin irritation and keeps the child in the water.

    If you are unsure if your child’s rash is from chlorine, from another cause like a fungal infection or heat rash, or from something in the pool environment like an allergic reaction to a different chemical, a clinical evaluation clarifies the diagnosis and avoids mistreatment.

    Frequently Asked Questions About Chlorine and Kids’ Skin

    Can Chlorine Cause an Allergic Reaction?

    True chlorine allergy is rare. What most people call a chlorine allergy is contact irritation caused by the stripping of the skin barrier. The symptoms, redness, itching, and dryness, overlap with an allergic response but are driven by irritation rather than an immune reaction. A dermatologist can determine which mechanism is at play through patch testing if needed.

    How Long Should Kids Stay in a Chlorinated Pool?

    There is no strict time limit, but longer sessions mean more chemical exposure. For children with sensitive skin, limiting continuous pool time to 60 to 90 minutes and rinsing afterward is a practical approach. Breaks out of the water allow the skin to recover and reduce cumulative chlorine skin irritation during the session.

    Is It Safe for Babies to Swim in Chlorinated Pools?

    Pediatricians generally consider chlorinated pools safe for babies over six months of age. Infant skin is extremely thin and permeable, so keep sessions short, rinse immediately afterward, and apply a thick barrier moisturizer. Avoid pools where the chlorine smell is overwhelming, as that indicates high chemical concentration or poor ventilation.

    Does Chlorine Make Eczema Worse?

    For many children with eczema, yes. Chlorine disrupts the already-impaired skin barrier, inviting moisture loss and inflammation. Pre-swim barrier protection and immediate post-swim care can mitigate this. Some eczema patients tolerate pool water well with proper preparation, so individual response shapes the approach.

    Should Kids Wear a Rash Guard to Reduce Chlorine Exposure?

    Rash guards reduce the amount of skin in direct contact with pool water, which limits chlorine exposure on covered areas, and can prevent chlorine skin irritation. For children with widespread eczema or chronic irritation, wearing a rash guard during swim practice or recreational swimming is a simple, effective protective measure.

    Summer pool time is one of the highlights of childhood, and chlorine irritation does not have to cut it short. With the right preparation and aftercare, most children can swim regularly without persistent skin problems. When home measures are not enough, the pediatric dermatology team at Chattanooga Skin and Cancer Clinic’s Cleveland location is here to help. We see patients at 3891 Adkisson Drive, Cleveland in Cleveland, Monday through Thursday. Call 423.479.8648 to schedule an appointment.

  • What Does a Dermatologist Really Treat? 10 Conditions Most People Don’t Know About

    What Does a Dermatologist Really Treat? 10 Conditions Most People Don’t Know About

    What Does a Dermatologist Really Treat? 10 Conditions Most People Don’t Know About

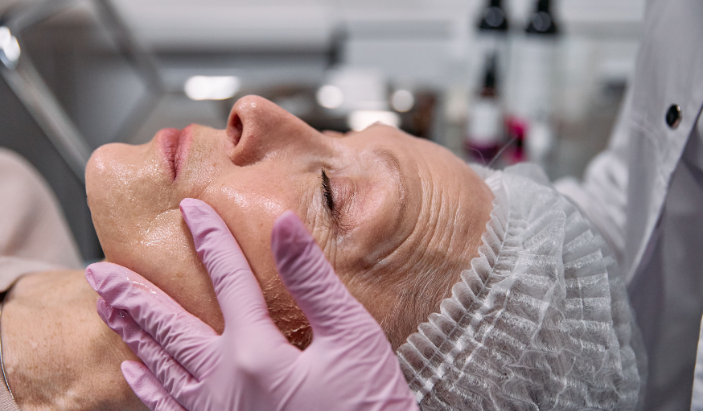
    A board-certified dermatologist conducting a professional medical skin evaluation on an adult patient's face at Chattanooga Skin and Cancer Clinic.
    Board-certified providers offer clinical evaluations for a wide range of chronic and acute skin conditions in Southeast Tennessee.

    Most people make their first dermatology appointment for one of two reasons: a suspicious spot they have been watching, or acne that will not clear up no matter what they try. Both are completely valid reasons to come in. The part that surprises most new patients is what they learn once they are there.

    Dermatology covers a wide range of conditions affecting the skin, hair, and nails. Skin cancer screenings and acne treatment are part of it, but so are chronic inflammatory conditions, hair loss, nail disorders, rashes that have defied every over-the-counter remedy, and conditions that started in childhood and followed a person into adulthood. Dermatologists are medical specialists with years of training specifically in skin health, which means the scope of what they diagnose and treat is considerably broader than most patients expect.

    At Chattanooga Skin and Cancer Clinic, patients have been coming in since 1973 for exactly that reason. Some know what they need. Others arrive with a condition their primary care doctor referred them for, or a symptom they have been trying to manage on their own. This post walks through what dermatologists treat, why some conditions belong in a specialist’s office rather than a general practitioner’s, and what patients in the Chattanooga area can expect when they come in.


    What Is a Dermatologist and How Is Their Training Different?

    A dermatologist is a physician who completed medical school, then spent three or more additional years in a dermatology residency focused entirely on skin, hair, and nail conditions. That residency includes surgical training, dermatopathology, and exposure to thousands of conditions ranging from common to rare. Board certification follows a rigorous examination process.

    This level of specialization matters because the skin is the body’s largest organ, and its conditions are numerous. More than 3,000 distinct skin conditions exist, according to the American Academy of Dermatology. A primary care physician can identify and treat many of the most common ones, but conditions that are chronic, resistant to standard treatment, or require a visual and clinical expertise built through years of practice are best managed by a specialist.

    All providers at Chattanooga Skin and Cancer Clinic are board-certified, and the practice has been operating in Southeast Tennessee for over 50 years. That depth of experience shapes how providers approach everything from a first-time skin check to a complex surgical case.


    Does a Dermatologist Only Treat Skin Cancer?

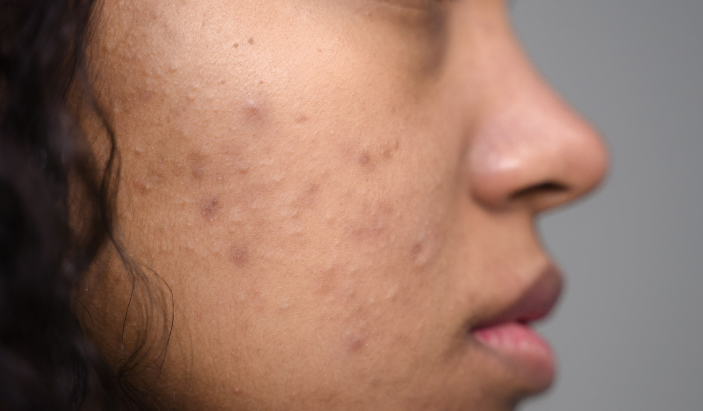
    Close-up of a patient with stubborn acne blemishes on their cheek seeking medical treatment from a dermatologist in Cleveland, TN.
    Persistent acne, driven by hormonal shifts or genetics, often requires a personalized prescription approach from a specialist.

    Skin cancer is one of the most important things a dermatologist diagnoses and treats, but it is far from the only one. The misconception that dermatology is primarily about cancer screenings keeps a lot of people from seeking care for conditions that are making their daily lives harder.

    Skin cancer detection and treatment, including Mohs micrographic surgery for basal cell and squamous cell carcinomas, is a core part of what the team at Chattanooga Skin and Cancer Clinic does. Mohs surgery is available at the Chattanooga and Cleveland locations and offers the highest cure rate for eligible skin cancers while preserving as much healthy tissue as possible. Melanoma screening, diagnosis, and treatment are also part of the practice’s focus.

    Outside of cancer, dermatologists manage a full range of medical conditions. Chronic inflammatory skin diseases like psoriasis, eczema, and rosacea require ongoing management that goes well past what an over-the-counter cream can provide. Acne, particularly adult acne driven by hormonal shifts, often needs a prescription approach that only a provider can prescribe. Rashes, allergic reactions, infections, warts, cysts, and moles all fall within a dermatologist’s scope of practice. So do hair loss, nail disorders, and conditions in children that can start as early as infancy.


    What Chronic Skin Conditions Can a Dermatologist Help Manage?

    Chronic conditions are where dermatology makes some of its most meaningful impact. These are conditions that do not go away on their own and that get worse without proper management. Living with one of them long-term without specialist care often means cycles of flare-ups, missed work, disrupted sleep, and real psychological strain.

    Is Psoriasis Something a Dermatologist Treats?

    A female dermatologist in a white coat explaining prescription biologics and targeted treatments to a patient in Chattanooga, Tennessee.
    Modern medical dermatology utilizes advanced targeted therapies and biologics to manage severe chronic skin conditions effectively.

    Psoriasis is an autoimmune condition that causes the skin to produce cells too rapidly, resulting in thick, scaly plaques that are often red, itchy, and uncomfortable. It shows up most often on the elbows, knees, scalp, and lower back, but it can appear anywhere on the body. Psoriasis is also associated with psoriatic arthritis, which affects joints and requires coordinated care.

    Treatment options have advanced considerably in recent years. Biologics and targeted therapies have given patients with moderate to severe psoriasis access to outcomes that were not possible even a decade ago. A dermatologist stays current on those options and can match the right treatment to the patient’s specific disease pattern, severity, and medical history.

    Can a Dermatologist Help With Eczema?

    Eczema, or atopic dermatitis, is one of the most common skin conditions in the United States, affecting about 31 million Americans according to the National Eczema Association. It causes dry, inflamed, itchy skin that can crack, bleed, and become infected when scratched. In children, it often appears on the face and in the skin creases. Adults tend to see it on the hands, neck, and inside of the elbows.

    Managing eczema well requires understanding a patient’s triggers, their skin barrier function, and the appropriate prescription options for their age and severity. The team at Chattanooga Skin and Cancer Clinic sees pediatric patients from infancy through adolescence and adult patients at all three locations. Consistent dermatology care for eczema reduces the frequency and severity of flares in a meaningful way.

    What About Rosacea?

    Rosacea is a chronic inflammatory condition that causes persistent facial redness, visible blood vessels, and sometimes acne-like bumps. It affects the cheeks, nose, forehead, and chin most often, and it is frequently mistaken for flushing or sensitive skin. Without treatment, rosacea progresses over time.

    Common triggers include heat, sun exposure, alcohol, spicy food, and stress. A dermatologist can confirm the diagnosis, identify a patient’s specific subtype, and recommend a combination of topical treatments, oral medications, and trigger management strategies. For patients in Chattanooga and the surrounding area, getting a definitive diagnosis from a board-certified provider is the starting point for effective long-term control.


    What Acute Conditions Bring Patients to a Dermatologist?

    Not every dermatology visit is about a chronic condition. Plenty of patients come in for something that developed recently and needs a prompt evaluation.

    Mole removal and evaluation is one of the most common acute reasons for a dermatology visit. A mole that has changed in size, shape, or color, or one that bleeds or itches without explanation, needs to be looked at by a trained eye. A dermatologist can examine the mole with a dermatoscope, determine whether a biopsy is necessary, and walk the patient through the results.

    Warts, cysts, and skin tags are also common reasons patients come in. These are benign growths, but they can be cosmetically bothersome, uncomfortable, or positioned in a way that causes irritation. Treatment options range from freezing to excision depending on the type and location. Rashes, allergic reactions, and skin infections round out the acute side of dermatology practice. Many patients come in after a rash has persisted for weeks without improvement, or after an over-the-counter treatment has made things worse rather than better. A provider can identify the underlying cause and prescribe the right course of action.


    Do Dermatologists Treat Children?

    Yes, and pediatric dermatology is an area where specialist care makes a significant difference. Children experience many of the same conditions as adults, but the presentation can differ, and treatment protocols are adjusted for age and developmental stage.

    Eczema is one of the most common pediatric skin conditions and one of the most underdiagnosed. Infants can develop it within the first few months of life. Warts, molluscum contagiosum, birthmarks, and scalp conditions are also common in children and teenagers. Acne in adolescents is another major area where a dermatologist provides real value, particularly when over-the-counter products have not produced results and the condition is starting to affect a young person’s confidence.

    At Chattanooga Skin and Cancer Clinic, pediatric and adolescent patients are seen at the Chattanooga and Cleveland locations. The practice has served families across the region for generations, which means a parent who came in as a teenager may now be bringing their own child in for care.


    When Should You See a Dermatologist Instead of Your Primary Care Doctor?

    Primary care physicians handle a wide range of skin issues well, and many straightforward cases can be managed at that level. A dermatologist is the right call when a condition is not responding to standard treatment, when it keeps coming back, when a visual evaluation from a trained specialist is needed, or when the patient wants access to the full range of treatment options including prescription biologics, surgical procedures, and advanced diagnostic tools.

    Annual full-body skin checks are something dermatologists do that general practitioners rarely perform in the same depth. A 15-minute full-body exam by a board-certified dermatologist covers areas a patient cannot easily see on their own, and it creates a documented baseline that makes future changes easier to identify. For patients over 35, for those with a family history of skin cancer, and for anyone who has spent significant time in the sun over the years, that annual check is worth making part of the regular health routine.

    Chattanooga Skin and Cancer Clinic accepts new patients at all three locations, in Chattanooga, Cleveland, and Kimball. No referral is required to schedule an appointment.


    Frequently Asked Questions

    Do I need a referral to see a dermatologist at Chattanooga Skin and Cancer Clinic? No. Chattanooga Skin and Cancer Clinic accepts new patients directly at all three locations without a referral. Appointments can be scheduled by calling the location nearest to you or visiting chattskinandcancer.com.

    What should I bring to my first dermatology appointment? Bring a list of your current medications and any supplements you take. Write down your skin concerns before the appointment, including how long each one has been present and what you have already tried. If you have a spot that comes and goes, take a photo of it when it is active. Coming with clean skin, free of heavy makeup or lotion in the areas you want evaluated, also helps the provider get the clearest view possible.

    Can a dermatologist help with hair loss? Yes. Hair loss has many causes, including autoimmune conditions, hormonal changes, nutritional deficiencies, and inflammatory scalp diseases. A dermatologist can evaluate the pattern and characteristics of hair loss, run relevant testing, and recommend treatment options. The scalp is skin, and scalp health is within a dermatologist’s scope of practice.

    How often should someone get a full-body skin check? For most adults, once a year is the standard recommendation. Patients with a personal or family history of skin cancer, a large number of moles, or significant past sun exposure may benefit from more frequent monitoring. Your provider at Chattanooga Skin and Cancer Clinic can recommend the right schedule based on your individual history during your first visit.

    Does Chattanooga Skin and Cancer Clinic see patients of all ages? Yes. The practice treats patients from infancy through elderly, making it a resource for the entire family. Pediatric and adolescent patients are seen at the Chattanooga and Cleveland locations. The Kimball location serves adult patients and handles medical dermatology conditions.

    What is the difference between medical and cosmetic dermatology? Medical dermatology focuses on diagnosing and treating conditions that affect health, including skin cancer, chronic inflammatory diseases, infections, and hair and nail disorders. Cosmetic dermatology focuses on aesthetic procedures like injectables and resurfacing treatments. Chattanooga Skin and Cancer Clinic is a medical dermatology practice. The providers focus on health-based care rather than cosmetic services.

  • Sunburn vs. Sun Poisoning: How to Tell the Difference and What to Do Next

    Sunburn vs. Sun Poisoning: How to Tell the Difference and What to Do Next


    You spent the day at the lake, maybe a little longer than planned. By evening, your skin is red and tender, and you feel run-down in a way that sleep alone does not seem to fix. Most people chalk that up to a bad sunburn and move on. Sometimes, though, what feels like a rough day in the sun is actually sun poisoning, a more serious reaction that calls for a different response.

    Sunburn and sun poisoning both result from overexposure to ultraviolet (UV) radiation. The difference comes down to severity and how your body reacts. Knowing which one you are dealing with helps you treat it properly and avoid complications that can turn a few uncomfortable days into a trip to urgent care or the dermatologist.


    What Is Sunburn, and Why Does It Happen?

    A woman with a severe sunburn on her shoulders sitting on a wooden bench by the water in Chattanooga, Tennessee.
    Spending a day out on the water can easily lead to severe UV damage and painful sunburns.

    Sunburn is the skin’s inflammatory response to UV radiation damage. When UV rays penetrate the skin, they damage the DNA in skin cells. The redness, warmth, and tenderness you feel are signs of that inflammation as your immune system responds to the injury.

    Symptoms of a typical sunburn include red or pink skin that is warm and sensitive to the touch, mild swelling, and peeling that begins a few days later as damaged skin cells shed. You may feel some fatigue and mild discomfort. These symptoms are generally confined to the skin itself. Most sunburns resolve on their own within three to five days with basic care.

    According to the Skin Cancer Foundation, a single blistering sunburn in childhood or adolescence more than doubles a person’s lifetime risk of developing melanoma. Even sunburns that do not blister accumulate damage over time. Repeated sunburns are one of the strongest preventable risk factors for skin cancer, which is why dermatologists take UV exposure so seriously.


    What Makes Sun Poisoning Different?

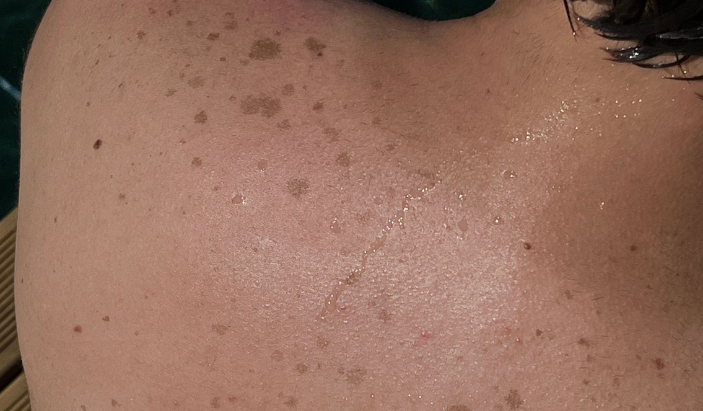
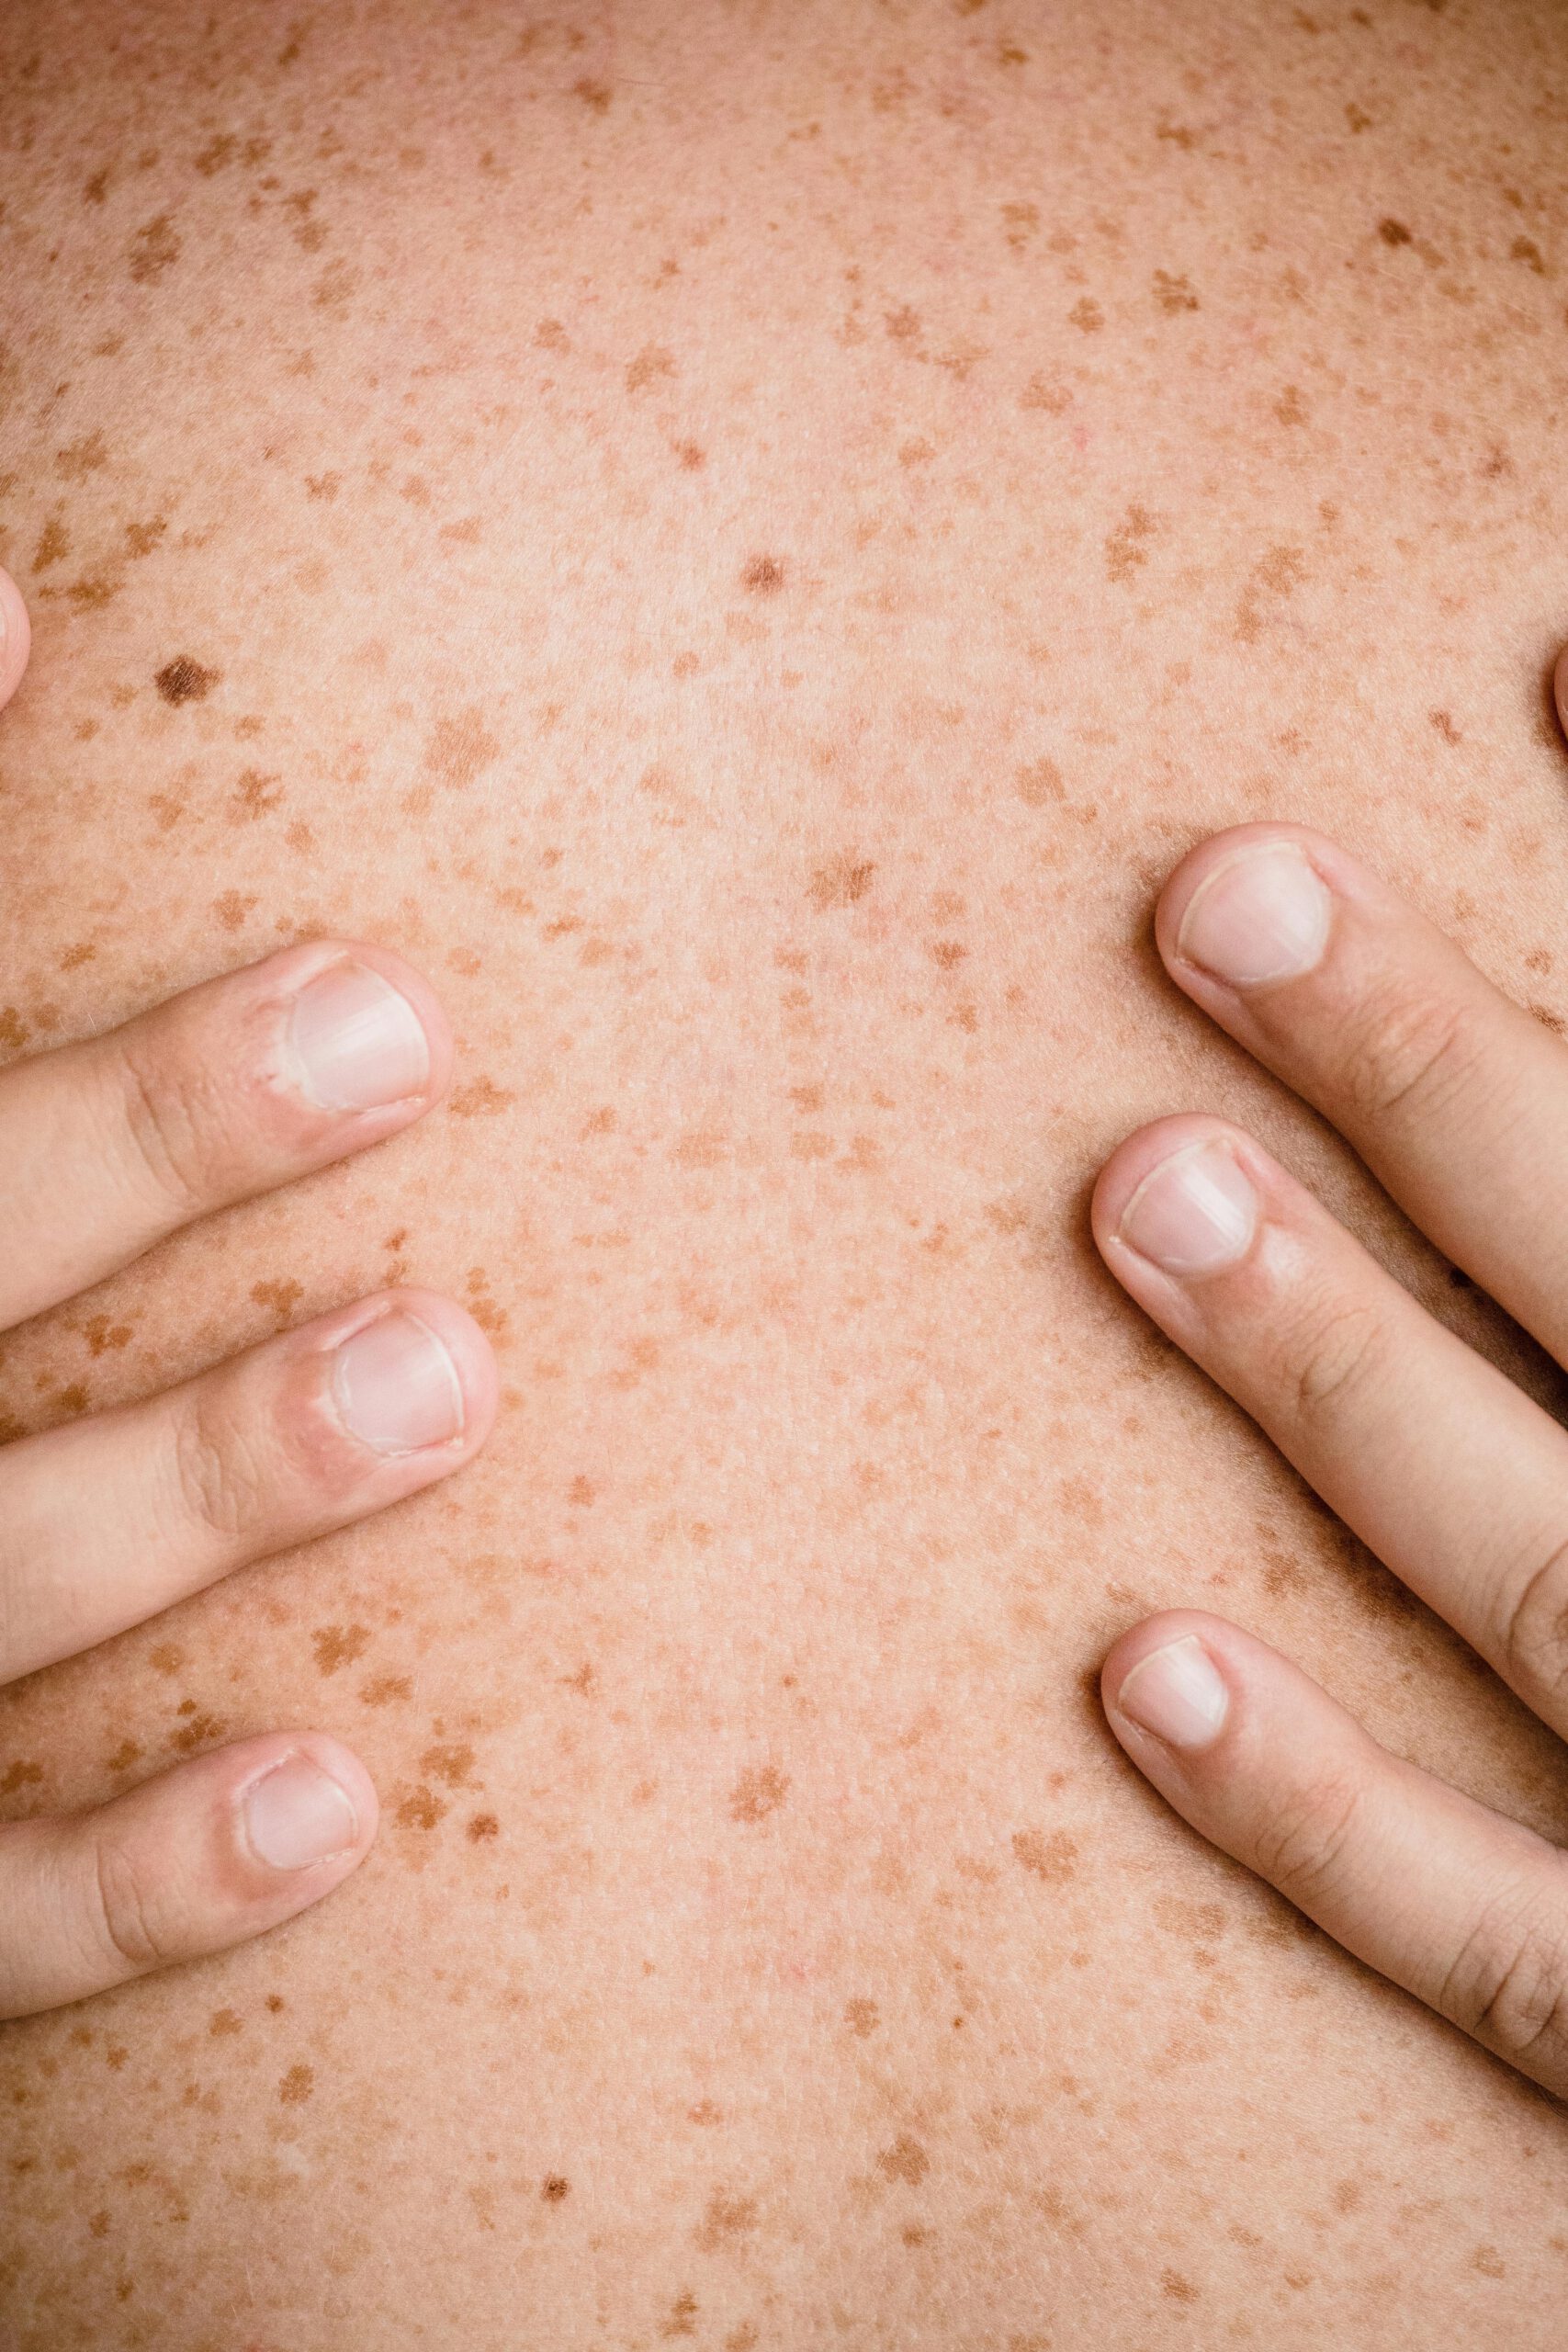
    Close-up of sun-damaged skin on a person's upper back with sun spots and freckles, highlighting the need for a dermatology screening in Kimball TN.
    Repeated UV exposure causes cumulative DNA damage, often resulting in sun spots, peeling, or changing moles.

    Sun poisoning is not a poisoning in the medical toxicology sense. The term refers to a severe sunburn that triggers a systemic reaction, meaning your body responds beyond the skin. Some people call it photodermatitis or polymorphous light eruption (PMLE), though those conditions involve specific immune reactions to sunlight and can differ from a straightforward overexposure reaction.

    The skin symptoms are more severe than a typical sunburn. Blistering, intense swelling, and skin that looks tight or leathery are common. The defining feature of sun poisoning, though, is that you feel sick. Nausea, vomiting, headache, dizziness, and fever separate sun poisoning from ordinary sunburn. Chills, dehydration, and in serious cases, a rapid heart rate or confusion can accompany these symptoms.

    Some people also develop a rash of small bumps or hives, which points toward an immune-mediated response to sun exposure. Fair-skinned individuals, people spending long hours outdoors at high altitudes or near reflective surfaces like water and snow, and those taking medications that increase sun sensitivity face higher risk.


    How Do You Tell the Two Apart?

    The clearest signal is how you feel overall. A sunburn hurts and looks bad, but you still feel relatively normal otherwise. Sun poisoning crosses into feeling genuinely ill. If you have nausea, a fever, dizziness, or a severe headache on top of your skin symptoms, sun poisoning is the more likely explanation.

    Look at the skin, too. Sunburn produces an even redness across the exposed area. Sun poisoning often brings blistering, significant swelling, or a rash pattern that looks unusual compared to regular redness. If the skin appears wet, oozing, or blistered across a large area of the body, that is a sign the reaction has gone beyond a mild sunburn.

    The timeline matters as well. Sunburn symptoms peak around 24 to 36 hours after exposure and then start to improve. Sun poisoning symptoms can intensify over the first day or two and take considerably longer to resolve. If things seem to be getting worse instead of better after 48 hours, that is worth paying attention to.


    What Should You Do If You Have a Sunburn?

    Treating a standard sunburn starts with cooling and hydration. Get out of the sun immediately and stay out. Cool (not cold) showers or compresses can reduce heat and discomfort in the skin. Drink extra water because UV radiation dehydrates the body even when you do not feel thirsty.

    Apply a fragrance-free moisturizer or aloe vera gel to the affected skin. Aloe has mild anti-inflammatory properties and can ease discomfort. Avoid products with added fragrances, alcohol, or numbing agents like benzocaine, which can irritate damaged skin or cause allergic reactions. Over-the-counter ibuprofen or naproxen helps reduce inflammation and pain and works better for sunburn than acetaminophen alone.

    Do not pop blisters if they form. Blisters are the skin’s natural protective barrier over the damaged area. Breaking them opens the wound to infection. If blisters do develop, keep the area clean and covered with a non-stick bandage. Once the skin starts peeling, let it happen on its own rather than pulling it off prematurely.


    What Should You Do If You Have Sun Poisoning?

    Sun poisoning with mild systemic symptoms, such as a slight headache and nausea, can often be managed at home with aggressive hydration, rest, and the same topical care used for sunburn. The key difference is that dehydration is a real risk. Water and electrolyte drinks are both important. If you cannot keep fluids down because of vomiting, that changes the situation.

    Seek medical attention if you have a fever above 103 degrees Fahrenheit, severe or spreading blisters, confusion or extreme dizziness, a rapid heartbeat, or if you are unable to stay hydrated due to persistent vomiting. Children, older adults, and anyone with a compromised immune system should seek care sooner rather than waiting to see if symptoms improve.

    Emergency care is appropriate for anyone showing signs of heat stroke alongside sun poisoning: confusion, loss of consciousness, no sweating despite extreme heat, or skin that looks gray or mottled. Heat stroke is life-threatening and requires immediate intervention.


    When Should You See a Dermatologist After Sun Exposure?

    A single bad sunburn may not require a dermatology visit, but several situations do. If you notice a rash that keeps returning with sun exposure, that points toward polymorphous light eruption or another photosensitivity condition, and a board-certified dermatologist can diagnose it and outline a management plan.

    Any new or changing spot on sun-damaged skin deserves a professional look. Repeated sun exposure increases the risk of basal cell carcinoma, squamous cell carcinoma, and melanoma, the three most common types of skin cancer. Catching these early makes treatment far more straightforward. Dermatologists recommend annual skin checks for anyone with a history of significant sun exposure, multiple sunburns, or a family history of skin cancer.

    If you live in the Chattanooga area, Chattanooga Skin and Cancer Clinic has provided medical dermatology care since 1973. The practice’s board-certified dermatologists see patients at three locations, including Chattanooga, Cleveland, and Kimball, and offer skin cancer screenings, mole evaluation, and treatment for chronic skin conditions.


    How Do You Protect Your Skin From UV Damage Going Forward?

    A close-up of a person applying sunscreen to a sun-exposed shoulder near the water, promoting skin cancer prevention.
    Applying broad-spectrum sunscreen is the most effective way to prevent both regular sunburn and systemic sun poisoning.

    The best defense against both sunburn and sun poisoning is consistent sun protection. Broad-spectrum sunscreen with SPF 30 or higher, applied 15 to 30 minutes before going outside and reapplied every two hours (or after swimming or sweating), forms the foundation of that protection. Most people apply far less sunscreen than needed for adequate coverage. Be generous on the face, neck, ears, and hands, which tend to accumulate the most UV exposure over a lifetime.

    UV-protective clothing, wide-brimmed hats, and sunglasses add another layer of defense, especially during peak UV hours between 10 a.m. and 4 p.m. Shade helps during those hours. Reflective surfaces like water, sand, and concrete intensify UV exposure even when cloud cover makes the day feel mild, so sun protection applies on overcast days as well.

    Certain medications, including some antibiotics, antihistamines, and diuretics, increase photosensitivity. If you take any prescriptions and plan to spend extended time outdoors, ask your doctor or pharmacist whether extra precautions make sense.


    Frequently Asked Questions About Sunburn and Sun Poisoning

    Can you get sun poisoning on a cloudy day?

    Yes. Up to 80 percent of UV rays pass through cloud cover. Overcast skies reduce but do not block UV radiation, and many serious sunburns and sun poisoning cases happen on cloudy days when people skip sunscreen because the sun does not feel intense.

    How long does sun poisoning last?

    Mild cases often resolve within two to three days. More severe cases with significant blistering or systemic symptoms can last up to a week or longer. If symptoms persist beyond a week or worsen after the first couple of days, see a doctor.

    Does tanning prevent sunburn?

    A tan offers minimal protection, roughly equivalent to an SPF of 2 to 4. It does not prevent UV damage. Each tanning session adds to cumulative DNA damage in the skin, which raises long-term skin cancer risk regardless of whether it results in a burn.

    Are some people more prone to sun poisoning?

    Fair-skinned individuals with less natural melanin face higher risk. People with a personal or family history of photosensitivity reactions, those at high altitudes, and anyone taking photosensitizing medications are also more susceptible. A history of previous sun poisoning episodes is one of the strongest predictors of future episodes.

    When does a sunburn require emergency care?

    Head to the emergency room or call 911 if you experience confusion, loss of consciousness, a rapid or irregular heartbeat, inability to keep fluids down, or signs of heat stroke alongside severe skin symptoms. These are medical emergencies that go beyond what at-home care can address.

    How does sun exposure contribute to skin cancer risk?

    UV radiation damages the DNA in skin cells, and that damage accumulates with each exposure. When DNA repair mechanisms cannot keep up, mutations can develop that lead to uncontrolled cell growth, which is how skin cancer forms. Melanoma, basal cell carcinoma, and squamous cell carcinoma are all strongly linked to UV exposure history.

    Should I schedule a skin check after a severe sunburn?

    A severe sunburn, especially one that blisters, is a reasonable prompt to schedule a baseline skin check with a dermatologist, particularly if you have other risk factors like fair skin, many moles, or a family history of skin cancer. Annual skin cancer screenings are a smart habit for anyone with a history of significant UV exposure.


    Sun damage adds up over a lifetime, and the choices you make now affect your skin health for years to come. If you are overdue for a skin check or have concerns about spots, moles, or a history of sunburns, Chattanooga Skin and Cancer Clinic is accepting new patients at all three locations. The clinic’s board-certified dermatologists specialize in medical dermatology and skin cancer detection, with more than 50 years of experience serving the greater Chattanooga region. Call 423-899-2700 to schedule in Chattanooga, 423-479-8648 in Cleveland, or 423-815-9975 in Kimball.

  • What Is Actinic Keratosis and Can It Turn Into Skin Cancer?

    What Is Actinic Keratosis and Can It Turn Into Skin Cancer?

    Actinic keratosis (AK) is a rough, scaly patch of skin caused by years of sun exposure, and yes, it can turn into skin cancer. Specifically, untreated actinic keratoses can progress into squamous cell carcinoma (SCC), the second most common type of skin cancer. The progression rate for any individual AK is estimated at about 5% to 10% over a 10-year period, according to research published in the Journal of Clinical and Aesthetic Dermatology. That percentage may sound low for a single spot, but most people who develop one AK have several, which multiplies the cumulative risk. Actinic keratoses are considered precancerous, meaning they are not cancer yet but have the potential to become cancer if left untreated. The good news is that treatment is straightforward, effective, and can be done in your dermatologist’s office. At Chattanooga Skin and Cancer Clinic, our board-certified dermatologists diagnose and treat actinic keratoses daily across our Chattanooga, Cleveland, and Kimball locations. Catching and treating these spots early is one of the most direct ways to prevent squamous cell carcinoma from developing in the first place.

    What Does Actinic Keratosis Look Like?

    Actinic keratoses are easier to feel than to see, at least in their earliest stages. They often start as small, rough patches that feel like sandpaper when you run your finger over them. The texture is the giveaway. Visually, they can appear as flat or slightly raised spots that are pink, red, tan, or flesh-colored. Some develop a hard, wart-like surface, and others have a white or yellowish crusty scale on top.

    They show up almost exclusively on sun-exposed skin: the face, scalp (especially in people with thinning hair), ears, neck, forearms, and backs of the hands. If you spend a lot of time outdoors or have a history of sunburns, these are the areas to watch.

    One tricky thing about AKs is that they can come and go. A rough patch might appear, flatten out or seem to disappear for a few weeks, then return. This intermittent pattern leads some people to dismiss them as dry skin or minor irritation. The difference is that dry skin responds to moisturizer. Actinic keratosis does not.

    Who Is Most at Risk for Developing Actinic Keratoses?

    Cumulative UV exposure is the primary driver. People who have spent decades in the sun, whether through outdoor work, recreation, or living in sunny climates, have the highest risk. Fair-skinned individuals with light eyes and hair are especially vulnerable because they have less melanin to absorb UV radiation, but actinic keratoses can develop in people of any skin tone.

    Age is a strong predictor. AKs become increasingly common after age 40, and by age 60 to 70, they’re one of the most frequent reasons for dermatology visits. Men develop them more often than women, likely due to historical differences in occupational sun exposure and lower rates of sunscreen use, though that gap has been narrowing.

    Other risk factors include a history of frequent sunburns (especially blistering sunburns in childhood or adolescence), tanning bed use, a weakened immune system (organ transplant recipients, people on immunosuppressive medications), and previous actinic keratoses or skin cancer. If you’ve had one AK, there’s a strong chance you’ll develop more over time.

    How Does Actinic Keratosis Progress to Squamous Cell Carcinoma?

    The progression from AK to SCC happens on a cellular level. UV radiation damages the DNA in skin cells called keratinocytes. When enough mutations accumulate, the cells begin to grow abnormally. In the AK stage, this abnormal growth is confined to the upper layer of the skin (the epidermis). The cells look atypical under a microscope, but they haven’t invaded deeper tissue.

    If the damaged cells continue to multiply and eventually break through the basement membrane (the boundary between the epidermis and the dermis), the condition is reclassified as squamous cell carcinoma. At that point, it’s no longer precancerous. It’s cancer.

    There’s no reliable way to predict which specific AKs will progress and which ones won’t. That unpredictability is exactly why dermatologists recommend treating all of them rather than adopting a wait-and-see approach. Treating a precancerous spot is simpler, cheaper, and less invasive than treating a skin cancer.

    What Are the Treatment Options for Actinic Keratosis?

    Several effective treatments exist, and the right one depends on how many AKs you have, where they are, and how thick they are.

    Cryotherapy (liquid nitrogen) is the most common treatment for individual or scattered AKs. Your dermatologist sprays liquid nitrogen directly onto the spot, which freezes and destroys the abnormal cells. It takes about 10 to 15 seconds per spot, stings briefly, and the treated area forms a blister or scab that heals within one to three weeks. No anesthesia is needed, and you can go back to normal activities immediately.

    For patients with many AKs spread across a larger area (a situation dermatologists call “field cancerization”), topical medications are often a better approach. Fluorouracil (5-FU) is a cream applied at home over two to four weeks that causes AKs to become red and inflamed before they peel off and heal. The treated area looks worse before it looks better, but the end result is healthier skin with fewer precancerous cells. Imiquimod is another topical option that stimulates the immune system to target abnormal cells.

    Photodynamic therapy (PDT) is a third option that combines a light-sensitizing solution with a special light source. The solution is applied to the skin, allowed to absorb for one to two hours, then activated with blue or red light. The reaction destroys AK cells while sparing normal tissue. PDT is available at our Chattanooga and Cleveland offices. It’s not offered at our Kimball location.

    Does Treatment Hurt, and What Is Recovery Like?

    Cryotherapy produces a brief stinging or burning sensation that lasts a few seconds during treatment. The spot may be tender for a day or two afterward. Most patients describe it as tolerable and quick.

    Topical treatments like fluorouracil cause redness, peeling, crusting, and sometimes discomfort over the course of treatment. The skin can look raw and irritated, particularly during the second and third weeks. This is expected and means the medication is working. Once treatment ends, the skin heals within two to four weeks, and the result is smoother, healthier-looking skin.

    Photodynamic therapy can cause moderate stinging or burning during the light activation phase, and the treated skin may remain red and sensitive for several days afterward. Sun avoidance for 48 hours after PDT is critical because the skin is temporarily hypersensitive to light.

    None of these treatments require downtime in the traditional sense. You can return to work and daily activities the same day, though you may want to plan topical treatment cycles around social events since the visible redness can be noticeable.

    Can Actinic Keratoses Come Back After Treatment?

    Yes. Treatment removes existing AKs, but it doesn’t undo the underlying sun damage in the surrounding skin. New actinic keratoses can develop in the same areas over time, particularly if sun exposure continues. Think of treatment as addressing the current problem while ongoing sun protection prevents the next one.

    Most patients with a history of AKs benefit from regular follow-up appointments (every 6 to 12 months) so new spots can be caught and treated while they’re still small and simple. Some dermatologists also recommend periodic field therapy (a round of topical treatment over a larger area) as a maintenance strategy for patients who develop frequent recurrences.

    How Can You Prevent Actinic Keratoses From Developing?

    Sun protection is the most effective prevention. That means daily broad-spectrum sunscreen with SPF 30 or higher on exposed skin, reapplied every two hours when outdoors. Protective clothing, wide-brimmed hats, and UV-blocking sunglasses reduce exposure to the areas where AKs most commonly develop. Seeking shade during peak UV hours (10 a.m. to 4 p.m.) makes a measurable difference as well.

    It’s worth noting that the sun damage causing today’s actinic keratoses happened years or even decades ago. You can’t undo past exposure, but you can stop adding to it. People who adopt consistent sun protection habits after their first AK diagnosis develop fewer new ones going forward. Prevention isn’t a retroactive fix, but it absolutely changes the trajectory.

    Frequently Asked Questions About Actinic Keratosis

    Is actinic keratosis the same as skin cancer?

    No. Actinic keratosis is a precancerous condition, meaning it has the potential to develop into squamous cell carcinoma but has not done so yet. Treating AKs removes that risk before cancer develops.

    How many actinic keratoses is too many?

    There’s no specific number that triggers alarm, but having multiple AKs across a sun-exposed area (called field cancerization) suggests widespread sun damage and a higher cumulative risk. Your dermatologist may recommend field therapy (topical treatment or PDT over a larger area) rather than treating spots individually.

    Where can I get actinic keratoses treated near Chattanooga?

    Chattanooga Skin and Cancer Clinic treats actinic keratoses at all three locations: Chattanooga (6061 Shallowford Road, 423-899-2700), Cleveland (3891 Adkisson Drive, 423-479-8648), and Kimball (400 Dixie Lee Center Rd, 423-815-9975). Cryotherapy is available at all locations. Photodynamic therapy is offered at Chattanooga and Cleveland.

  • When Should You See a Dermatologist About a Mole?

    When Should You See a Dermatologist About a Mole?

    Most moles are completely harmless, but some can be early signs of melanoma, the most serious form of skin cancer. You should see a dermatologist about a mole if it’s changing in size, shape, or color, if it looks noticeably different from your other moles, if it bleeds or itches without a clear reason, or if it appeared recently and is growing. The average adult has between 10 and 40 moles, according to the American Academy of Dermatology, and the vast majority of them will never cause a problem. But melanoma can develop in an existing mole or show up as a brand-new spot, and the difference between a harmless mole and an early melanoma isn’t always obvious to the untrained eye. That’s why knowing what to watch for, and knowing when to pick up the phone, matters. At Chattanooga Skin and Cancer Clinic, our board-certified dermatologists evaluate moles and suspicious spots every day across our Chattanooga, Cleveland, and Kimball offices. A quick evaluation can either put your mind at ease or catch something early when treatment is simplest.

    What Does a Normal Mole Look Like?

    A normal mole is usually a small, round or oval spot on the skin that’s one uniform color, typically brown, tan, or flesh-toned. It has smooth, well-defined borders, and it stays roughly the same size and shape over time. Most moles appear during childhood and adolescence, and it’s normal for them to darken slightly during pregnancy or with sun exposure.

    Normal moles can be flat or raised. They can be tiny dots or up to about a quarter-inch across. Some have hair growing from them, which is actually a reassuring sign because melanoma rarely grows hair. The defining characteristic of a normal mole is stability. It looks the same month after month, year after year.

    That stability is exactly what you’re tracking when you do monthly self-skin checks. Once you know what your moles normally look like, a change stands out.

    What Makes a Mole Suspicious?

    Dermatologists use the ABCDE criteria to evaluate whether a mole warrants a closer look. Asymmetry: one half of the mole doesn’t mirror the other. Border irregularity: the edges are jagged, scalloped, or blurred rather than smooth. Color variation: multiple shades of brown, black, red, white, or blue within a single mole. Diameter: the spot is larger than 6 millimeters (roughly the size of a pencil eraser), though melanomas can be smaller. Evolution: the mole is changing in any way, whether that’s size, shape, color, elevation, or texture.

    Of these five, evolution is the most clinically useful. A mole that was stable for 20 years and suddenly starts growing, darkening, or developing an irregular border is worth a visit regardless of whether it checks every other box. Change is the signal.

    There’s also the “ugly duckling” sign: a mole that looks distinctly different from all the others on your body. Most of a person’s moles tend to share a general family resemblance. If one spot is clearly the outlier, it deserves attention.

    Can a Mole Turn Into Melanoma?

    Yes, though most melanomas actually arise as new spots rather than from existing moles. A study published in the Journal of the American Academy of Dermatology found that roughly 70% of melanomas develop on previously normal-appearing skin, while about 30% arise from pre-existing moles. This means both new spots and changing old ones need monitoring.

    When melanoma does develop within an existing mole, it typically causes visible changes: the mole gets larger, its color becomes uneven, its border becomes irregular, or it starts to feel different (itching, tenderness, or a sensation of firmness underneath). These changes usually happen over weeks to months rather than overnight.

    The good news is that melanoma caught at its earliest stage (melanoma in situ, confined to the outer layer of skin) has a nearly 100% five-year survival rate. Catching it at a later stage, after it has grown deeper, drops that rate considerably. The thickness of the melanoma at the time of diagnosis is the single strongest predictor of outcome, which is why speed matters.

    What Happens When a Dermatologist Evaluates a Mole?

    The evaluation is quick and painless. Your dermatologist will look at the mole with the naked eye first, then use a dermatoscope, a handheld magnifying device with polarized light that reveals structures beneath the skin surface that aren’t visible otherwise. Dermatoscopy has been shown to improve diagnostic accuracy for melanoma by 20% to 30% compared to examination without magnification.

    Based on the dermatoscopic pattern, your dermatologist will either reassure you that the mole looks benign, recommend monitoring it over time with serial photographs, or recommend a biopsy. If a biopsy is recommended, it’s done in the office that same day.

    A skin biopsy involves numbing the area with a small injection and then removing part or all of the mole. The tissue is sent to a dermatopathologist (a specialist in diagnosing skin diseases under a microscope), and results typically come back within one to two weeks. If the biopsy shows melanoma or another concern, your dermatologist will walk you through next steps, which may include a wider excision or referral to an oncologist depending on the depth and type.

    Do Atypical Moles Always Become Cancer?

    No. Atypical moles (also called dysplastic nevi) are moles that look unusual under the microscope but aren’t melanoma. They tend to be larger than normal moles, with irregular borders and uneven coloring. Having atypical moles does increase your statistical risk of developing melanoma over your lifetime, but most atypical moles never become cancerous.

    Think of it this way: atypical moles are a risk marker, not a guarantee. Someone with many atypical moles and a family history of melanoma should be monitored more closely (typically every six months rather than annually), but there’s no reason to panic about every unusual-looking spot.

    Your dermatologist can help you sort out which of your moles need monitoring, which can be left alone, and which should be removed. That kind of personalized risk assessment is hard to replicate on your own, which is another reason professional exams matter.

    Are There Mole Changes That Are Not Concerning?

    Yes. Moles can change in ways that are completely benign. During puberty, moles may darken or grow slightly. During pregnancy, hormonal changes can cause moles to become darker or larger temporarily. As people age, moles sometimes lose color and become flesh-toned or slightly raised. A mole that was flat in your 20s and becomes slightly dome-shaped in your 50s is following a normal aging pattern.

    Irritation from clothing, shaving, or friction can also cause a mole to become red, tender, or slightly swollen. If the irritation resolves within a week or two and the mole returns to its normal appearance, that’s usually nothing to worry about.

    The distinction comes down to pattern versus persistence. A mole that changes briefly due to an obvious external cause and then returns to baseline is different from a mole that is progressively changing over weeks without a clear trigger. When in doubt, a professional opinion takes the guesswork out of it.

    How Can You Keep Track of Your Moles Over Time?

    The most practical method is a combination of monthly self-checks and photography. Pick one day each month and examine your skin head to toe in a well-lit room with a full-length mirror and a hand mirror. Photograph any moles you want to track, placing a coin or ruler next to them for scale. Store the photos in a dedicated album on your phone so you can compare month to month.

    Some dermatology practices offer full-body photography and mole mapping, where every mole is professionally photographed and catalogued so that new or changed spots can be identified at subsequent visits. This is particularly useful for patients with a high mole count or a strong family history of melanoma.

    At Chattanooga Skin and Cancer Clinic, we work with patients to establish a monitoring plan that matches their individual risk level. For most people, that means annual professional exams combined with monthly self-checks at home. For higher-risk patients, it may mean exams every three to six months.

    Frequently Asked Questions About Moles and Melanoma

    Should I be concerned about moles my children have?

    It’s normal for children to develop moles throughout childhood and adolescence. Most childhood moles are benign. However, if a mole on your child is rapidly growing, has multiple colors, or looks very different from their other spots, have a pediatric dermatologist or board-certified dermatologist evaluate it. Chattanooga Skin and Cancer Clinic treats patients of all ages, including children.

    Can a mole biopsy cause cancer to spread?

    No. This is a common myth. Biopsying a mole does not cause cancer to spread. A biopsy is the only way to determine whether a suspicious spot is cancerous, and delaying a biopsy out of fear gives a potential cancer more time to grow.

    Where can I have a mole evaluated near Chattanooga?

    Chattanooga Skin and Cancer Clinic evaluates moles at all three locations: Chattanooga (6061 Shallowford Road, 423-899-2700), Cleveland (3891 Adkisson Drive, 423-479-8648), and Kimball (400 Dixie Lee Center Rd, 423-815-9975). Appointments are available Monday through Friday.